Tumor / immune interface肿瘤与免疫细胞界面
PD-L1 on tumor cells can bind PD-1 on T cells and suppress T-cell activity. Anti-PD-1 or anti-PD-L1 antibodies can interrupt this checkpoint interaction.肿瘤细胞上的PD-L1可与T细胞上的PD-1结合,抑制T细胞活性。抗PD-1或抗PD-L1抗体可阻断这一免疫检查点相互作用。
RESEARCH EVIDENCE · 2026-10-16 · VERSION 1.0
A five-model observational analysis of 489 MSK-CHORD patients.基于489名MSK-CHORD患者的五模型观察性分析。
Internal M5 C-index = 0.6061. Modest incremental performance and incomplete external evidence do not support a validated individual treatment-benefit claim.M5内部C-index为0.6061。预测增量有限且外部证据未完成,尚不支持经验证的个体治疗获益主张。
489 LUAD patients: 302 deaths, 187 censored. All five models use the same patients. A smaller cell remains: PD-L1-negative / no named ICI, 33 patients and 13 deaths.489名肺腺癌患者:302例死亡、187人删失;五模型使用完全相同患者。PD-L1阴性且未记录ICI一格仍较小:33人、13例死亡。
| Pretreatment tumor PD-L1治疗前肿瘤PD-L1 | No named ICI recorded (T=0)未记录已命名ICI(T=0) | Named ICI recorded (T=1)记录已命名ICI(T=1) |
|---|---|---|
| Negative (P=0)阴性(P=0) | 33 / 13 / 20 | 87 / 59 / 28 |
| Positive (P=1)阳性(P=1) | 111 / 79 / 32 | 258 / 151 / 107 |
Documented stage IV before index; pretreatment PD-L1; no targeted/ADC in the initiation window; cohort entry by index + 28 days and observed survival beyond that landmark. OS time is remaining months from the landmark, not from diagnosis or randomization.治疗前记录为IV期;PD-L1在治疗前;起始窗口无记录靶向药/ADC;在治疗开始后28天landmark前进入观察,且观察超过该点。OS从landmark计算剩余月数,不是从诊断或随机分组计算。
T=0 means no named ICI in the initial window. Later ICI is possible. Research agents may conceal exposure. In the negative/T=0 cell, chemotherapy-only accounts for 11 patients/5 deaths; research agents 11/3; other drugs 11/5. A common chemotherapy backbone was not required.T=0仅指起始窗口未记录已命名ICI,后续仍可能用ICI;试验药也可能隐藏实际暴露。阴性T=0一格中,化疗only为11人/5死亡,试验药11/3,其他药11/5;未要求相同化疗基础。
PD-L1 on tumor cells can bind PD-1 on T cells and suppress T-cell activity. Anti-PD-1 or anti-PD-L1 antibodies can interrupt this checkpoint interaction.肿瘤细胞上的PD-L1可与T细胞上的PD-1结合,抑制T细胞活性。抗PD-1或抗PD-L1抗体可阻断这一免疫检查点相互作用。
The model uses the latest documented tumor-cell PD-L1 positive/negative result on or before the treatment index date. It does not measure PD-1 expression, a mutation-defined pathway state, or the entire pathway’s activity.模型使用治疗开始当日或之前最近一次记录的肿瘤细胞PD-L1阳性/阴性结果。它不是PD-1表达、由突变定义的通路状态,也不是完整通路活性。
| Model模型 | Inputs输入 | Question比较内容 |
|---|---|---|
| M1 | C | Clinical and background-treatment baseline临床及背景治疗基线 |
| M2 | C + P | Baseline + pretreatment tumor PD-L1基线 + 治疗前肿瘤PD-L1 |
| M3 | C + T | Baseline + index-window ICI exposure基线 + 起始窗口ICI记录 |
| M4 | C + P + T | Both main effects; no interaction同时加入两个主效应,无交互 |
| M5 | C + P + T + P × T | Main effects + biomarker–treatment interaction主效应 + 标志物与治疗交互 |
P is recorded tumor-cell PD-L1 positivity, not a genomic mutation or a full pathway activity signature. No uniform assay/TPS cutoff is inferred where source reports are heterogeneous. The 625-person historical feasibility cohort and the present 489-person cohort address different definitions.P是报告中的肿瘤细胞PD-L1状态,不是基因突变或完整通路活性特征;来源报告异质时不推定统一检测/TPS阈值。早期625人可行性队列与当前489人队列定义不同。
Primary baseline C1: sex; ECOG and missingness; pretreatment liver/brain documentation and recorded extra-pulmonary site categories over 90 days; no-site-documentation indicator; outside-MSK prior-treatment documentation over 365 days and missingness; index-window cisplatin. No-site documentation is not proof of absence. Cisplatin is not a complete chemotherapy adjustment.主基线C1:性别;ECOG及缺失;治疗前90天肝/脑文档及已记录肺外部位类别;无部位文档标记;治疗前365天院外既往治疗文档及缺失;起始窗口顺铂。无文档不证明没有转移,顺铂不能完整控制化疗差异。
Fixed Ridge Cox (alpha=1, Breslow), event-stratified 5-fold evaluation repeated 3 times; training-fold preprocessing only. Seeds: 20261016/17/18. No hyperparameter tuning in this round. Earlier cohort/definition exploration means the overall analysis remains exploratory.固定Ridge Cox(alpha=1、Breslow),按事件分层5折,重复3次;预处理仅在训练折估计。随机种子20261016/17/18。本轮未调参;此前经历多轮队列和定义探索,因此整体仍属于探索性研究。
| Model模型 | C-index ↑ | Brier 12m ↓ | Brier 24m ↓ | Calibration slope 24m*24月校准斜率* |
|---|---|---|---|---|
| M1 | 0.5994 | 0.2201 | 0.2446 | 0.553 |
| M2 | 0.6001 | 0.2160 | 0.2408 | 0.596 |
| M3 | 0.5973 | 0.2208 | 0.2453 | 0.547 |
| M4 | 0.5979 | 0.2167 | 0.2414 | 0.592 |
| M5 | 0.6061 | 0.2139 | 0.2367 | 0.668 |
C-index and IPCW Brier are averages across three repeats. Calibration slopes are first-repeat IPCW logistic estimates (ideal=1). The measures use the same patients but different summaries: the slope is not a three-repeat mean.C-index及IPCW Brier为三次重复均值;校准斜率为首轮IPCW逻辑校准估计(理想值1)。虽使用相同患者,统计汇总方式不同,校准斜率不是三轮均值。
Mean ΔC: M5 − M4 = +0.0082; M5 − M1 = +0.0067. Mean ΔBrier24: M5 − M4 = −0.0047. These are limited internal improvements, not external efficacy results.平均ΔC:M5−M4为+0.0082,M5−M1为+0.0067;平均ΔBrier24:M5−M4为−0.0047。属于有限的内部性能增量,不是外部疗效结果。
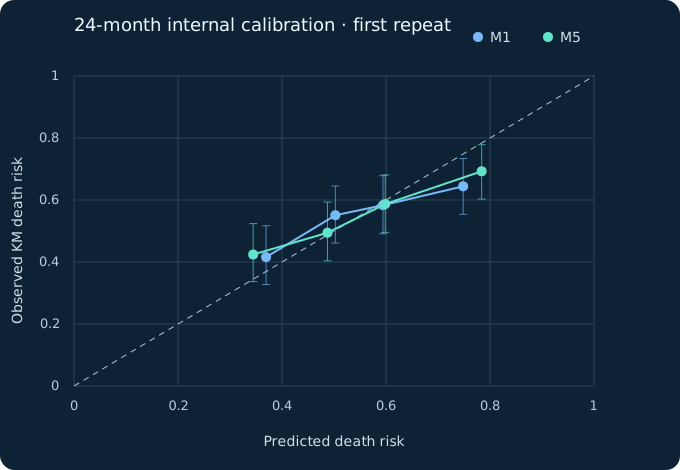
For M5 at 24 months: mean predicted death risk 55.32%, observed KM risk 54.81%, calibration slope 0.668. The mean aligns reasonably, while risk contrast remains miscalibrated.M5在24月:平均预测死亡风险55.32%,观察KM风险54.81%,校准斜率0.668。总体均值较接近,但风险差异的校准仍不足。
First-repeat paired conditional bootstrap (500 resamples): ΔC M5−M4 = +0.0093, 95% CI −0.0020 to +0.0214; ΔBrier24 = −0.0051, 95% CI −0.0102 to −0.0006. Predictions are held fixed; these intervals do not include model-refitting uncertainty. They refer to the first repeat, not the three-repeat averages above.首轮配对条件bootstrap(500次):ΔC M5−M4为+0.0093,95%CI为−0.0020至+0.0214;ΔBrier24为−0.0051,95%CI为−0.0102至−0.0006。固定预测不重拟合,区间不包含模型重拟合不确定性;它们对应首轮,不是上方三轮均值。
A separate unpenalized, full-cohort adjusted Cox model gives an interaction hazard-ratio ratio of 0.413 (95% CI 0.211–0.809), Wald p=0.0099. This inferential fit is separate from the penalized cross-validated prediction models.另行使用全队列无惩罚调整Cox模型,交互HR比为0.413(95%CI 0.211–0.809),Wald p=0.0099。该推断拟合与惩罚交叉验证预测模型分开。
ICI-associated HR: PD-L1-negative 2.196 (1.189–4.055), PD-L1-positive 0.906 (0.683–1.203). The signal is driven largely by a higher observed hazard in the negative group; the positive-group interval crosses 1. It does not establish causal harm in negative patients or benefit in positive patients.ICI相关HR:PD-L1阴性组2.196(1.189–4.055),阳性组0.906(0.683–1.203)。信号主要表现为阴性组观察死亡风险较高,阳性组区间跨1;不能据此推断阴性患者的因果伤害或阳性患者的获益。
Treatment selection, incomplete chemotherapy adjustment, exposure misclassification, source selection and other unmeasured confounding remain. The interaction p-value is exploratory; correction across two baseline variants does not account for the entire history of design exploration. A low p-value does not establish useful individual benefit prediction.仍存在治疗选择、化疗调整不足、暴露错分、来源选择和未测混杂。交互p值属于探索性结果;两套基线内校正未覆盖全部历史设计探索。p值较小不代表已具备有用的个体获益预测能力。
The named ICI category includes different checkpoint agents and combinations. PD-L1 is not the direct target of every agent in that category; treatment heterogeneity remains a limitation.已命名ICI类别包含不同检查点药物和联合用药;PD-L1并非该类别每种药物的直接靶点,治疗异质性仍是限制。
Completed: cohort audit, timed variable definitions, repeated internal evaluation, calibration and uncertainty reporting. Outstanding: compatible independent external evaluation of these exact five models and validation of treatment-benefit predictions.已完成:队列审计、变量时序定义、重复内部评估、校准与不确定性报告。待完成:这五个模型在兼容独立队列中的外部评估,以及治疗获益预测的验证。
A separate sex/ECOG simplified model was tested in two published trial datasets, with limited transfer performance. Those inputs, populations and treatment contrasts differ; that exercise does not validate the PD-L1 × ICI model. No external trial results are presented here as evidence for M5.另行使用两个已发表试验数据集测试了性别/ECOG简化模型,迁移表现有限;输入、人群及治疗比较不同,不能验证PD-L1×ICI模型。本报告未把外部试验结果作为M5验证证据。
Current decision: suitable as a transparent exploratory research and evidence-reporting case. Insufficient for an externally validated individual treatment-benefit product or patient-specific treatment recommendation.当前判断:可作为透明的探索性研究与证据交付案例;尚不足以作为经外部验证的个体治疗获益产品或患者用药推荐。
Analysis snapshot: MSK_CHORD_LUAD_489_PDL1_ICI_Models1_5_20261016.zip. Five-model primary C1 results; no patient-level records or individual predictions are distributed by this webpage.分析快照:MSK_CHORD_LUAD_489_PDL1_ICI_Models1_5_20261016.zip。展示五模型主分析C1结果;本页面不分发患者级记录或个体预测。
Research use only. No patient-specific medical advice. Public-data analyses do not imply endorsement by MSK, NCI or the data contributors.仅供科研使用,不提供个体医疗建议。公共数据分析不代表MSK、NCI或数据贡献方背书。